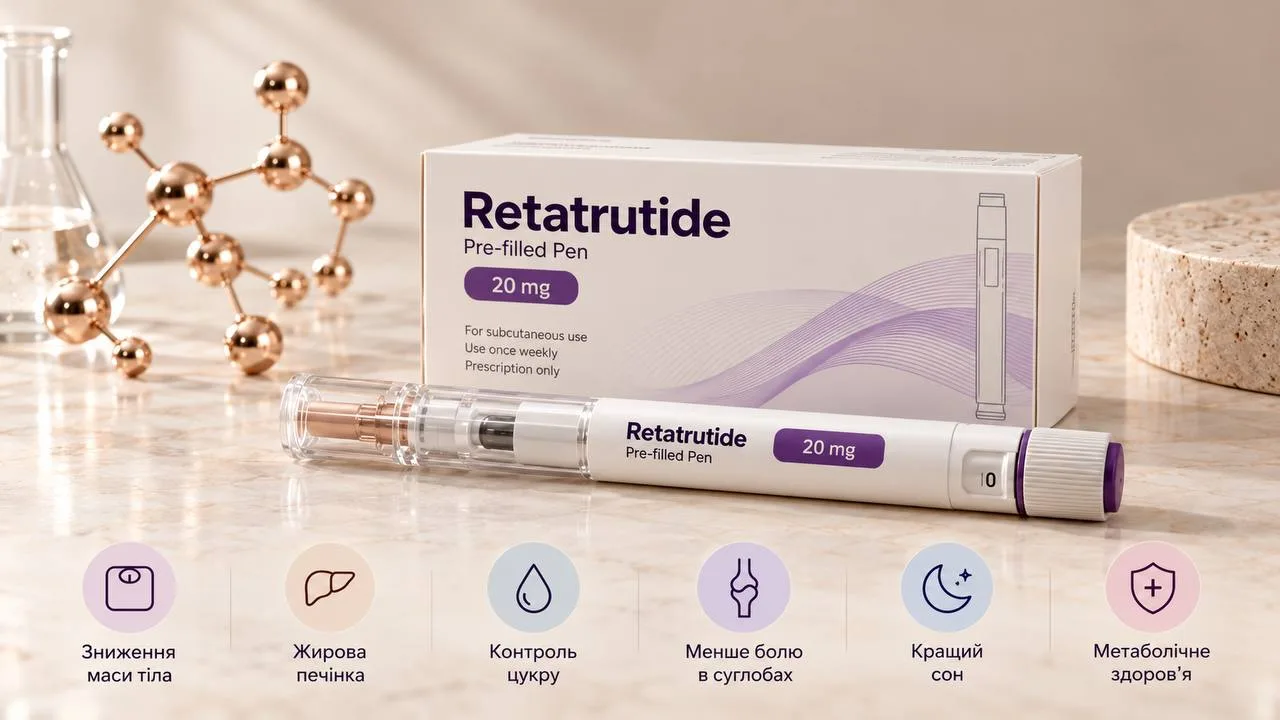
Why is the weight on Mundjaro, appetite returns and cravings for sweets? How do amylin, cagrilintide, tirzepatide and retatrutide work and how do they differ?
Amylin and kagrilintide: why appetite returns, weight stays the same and what are the differences between peptides for weight loss
“At first, the weight went down wonderfully, but then it stopped.”
“At the beginning of the treatment, I didn’t feel like eating at all, but now I crave sweets again.”
“Why did my friend lose 20 kg, and I hardly see any results?”
“Which is better for weight loss, Mundjaro, retatrutide or kagrilintide?”
These are questions that are increasingly being asked by people interested in modern weight control drugs.
And the reason is not always in willpower, the amount of food eaten, or the wrong drug.
Appetite regulation is a complex process involving the brain, intestines, pancreas, hormones, and satiety signals.
That is why today researchers are studying not only GLP-1, but also other mechanisms, including amylin and its long-acting analogue kagrilintide.
What is amylin and why is it being talked about?
Amylin is a natural peptide hormone that is produced by the beta cells of the pancreas along with insulin.
Its task is to participate in the regulation of satiety and metabolism after eating.
Amylin helps the body receive a signal that there is enough food. It also slows down the emptying of the stomach and affects the secretion of glucagon after eating.
That is, appetite is regulated not only by the feeling of hunger, but also by the body's ability to feel satiety in time.
It is this mechanism that became the basis for the development of new drugs that act through amylin receptors.
What is cagrilintide in simple words?
Cagrilintide (AM833) is a long-acting synthetic analogue of amylin, which is being studied for the treatment of obesity.
It interacts with amylin and calcitonin receptors, which are involved in the regulation of eating behavior and satiety.
To put it simply, researchers are interested in the possibility of influencing not only the feeling of hunger, but also the moment when a person feels that he has already eaten.
But it is important to understand: cagrilintide is not a universal remedy against overeating, emotional hunger or addiction to sweets.
Its effectiveness and safety are evaluated in clinical studies.
Why do people lose weight on Mundjaro at first, and then the weight stays the same?
A weight plateau is one of the most common reasons for disappointment during weight loss.
A person begins treatment, their appetite decreases, their weight gradually decreases. But after a few months, the number on the scales stops changing.
Why does this happen?
First, with a decrease in body weight, the body needs less energy to maintain vital functions.
Secondly, the result is affected by nutrition, physical activity, sleep, changes in body composition and concomitant diseases.
Third, a short-term weight loss plateau does not always mean a true plateau. Fluid retention, constipation, and fluctuations in the menstrual cycle can mask fat loss.
Sometimes a person has already achieved significant weight loss, but expects the rate to remain the same.
Therefore, a plateau on tirzepatide or semaglutide does not automatically mean that the drug has stopped working.
Why does appetite return on GLP-1?
Some people notice that at the beginning of treatment they were satisfied with a small portion, and then their appetite partially returned.
This does not necessarily mean that the entire therapeutic effect has been lost.
The feeling of satiety can change over time, and eating behavior is influenced by stress, lack of sleep, habits, and the food environment.
It is important to distinguish physiological hunger from situations where food becomes a way to cope with emotions.
That is why obesity treatment is not limited to appetite suppression alone.
Why do people constantly crave sweets, even when they are not hungry?
Cravings for sweets are not always a sign of insulin resistance.
They can be influenced by insufficient food intake during the day, strict restrictions, sleep, stress, habits and the brain's reward system.
GLP-1 drugs and amylin analogues are being studied for their effects on the regulation of appetite and eating behavior.
However, there is no reason to promise that cagrilintide will permanently eliminate the desire to eat sweets or solve the problem of emotional overeating.
If a person constantly thinks about food, it is important to evaluate not only the drug, but also the overall eating pattern and the reasons for such behavior.
Cagrilintide and semaglutide: what is CagriSema?
One of the most interesting areas of research is the combination of cagrilintide with semaglutide.
This combination is called CagriSema.
Semaglutide activates GLP-1 receptors, and cagrilintide affects the amylin system.
The idea is to use two different, partially complementary mechanisms of appetite and satiety control.
In the REDEFINE 1 study, the average weight loss in the CagriSema group was 20.4% at 68 weeks in an analysis that included participants regardless of whether they continued treatment.
This is the average result of the clinical trial, not a prediction for each individual.
As of October 2026, CagriSema remains an investigational combination, with the FDA's decision on the application pending.
Cagrilintide or tirzepatide - which is stronger?
Tirzepatide is a dual agonist of the GIP and GLP-1 receptors, which is used for approved indications depending on the country and dosage form.
Cagrilintide works through a different amylin and calcitonin receptors.
Therefore, it is not correct to compare them only by the percentage of weight lost.
In the REDEFINE 4 study, the CagriSema combination provided approximately 23% weight loss over 84 weeks, but did not meet the main condition of the study for non-inferiority compared to tirzepatide at the doses studied.
At the same time, the results of another study REIMAGINE 5 in people with type 2 diabetes showed the superiority of the studied lower dose of CagriSema over the lower dose of tirzepatide in terms of weight loss.
This means that the conclusion “one drug is always stronger” does not correspond to scientific data. The doses, patient group, duration of treatment and the purpose of the study are important.
Retatrutide - how is it different from amylin and cagrilintide?
Retatrutide is an investigational triple agonist of the GLP-1, GIP and glucagon receptors.
Its mechanism of action is different from both tirzepatide and cagrilintide.
Retatrutide is being investigated as a potential treatment for obesity and related metabolic conditions.
It has attracted attention for its significant weight loss in clinical trials, but the results do not mean that any product labeled Retatrutide has the same quality, efficacy, or safety.
Retatrutide and cagrilintide are not interchangeable.
Can amylin, cagrilintide, tirzepatide, or retatrutide be combined?
The idea of targeting multiple hormonal pathways simultaneously is being actively explored.
But that does not mean that combining different peptides on their own is safe.
For example, the CagriSema results cannot be extrapolated to combinations of cagrilintide with tirzepatide or retatrutide.
There is not enough clinical evidence to recommend these regimens for self-administration.
Combining substances that affect appetite and digestion may increase the risk of nausea, vomiting, constipation, dehydration, and malnutrition.
Why does stronger appetite suppression not always mean better weight loss?
Many people evaluate a drug by one criterion: how much it suppresses the desire to eat.
But complete lack of appetite is not necessarily the desired result.
When a person eats too little, their intake of protein, vitamins, and minerals can decrease. This poses risks to muscle mass, fitness, and treatment tolerance.
It is especially important to monitor the quality of nutrition during rapid weight loss.
The goal of obesity treatment is not simply to make a person stop eating, but to ensure sustainable health improvements.
Why does weight gain occur after weight loss drugs are discontinued?
After stopping treatment, appetite may increase, and the body continues to adapt to a lower body weight.
Obesity is often chronic, so regaining some of the weight after stopping therapy is a known risk.
This does not mean that a person will necessarily overeat or lack willpower.
That is why it is advisable to discuss a plan for maintaining the result before completing treatment.
There is currently no convincing evidence that switching to carglintide or another experimental peptide is guaranteed to prevent weight gain again.
What tests are important if weight does not decrease?
There is no single test that will explain all the reasons for the plateau.
Depending on the symptoms, history and concomitant diseases, the doctor may evaluate:
Glucose and HbA1c - to detect carbohydrate metabolism disorders.
Lipid profile - to assess cardiovascular risk.
TSH - if there are signs of thyroid dysfunction.
Liver and kidney function - according to clinical indications.
Deficiency indicators - if there are symptoms or risk factors.
Fasting insulin and HOMA-IR are not needed by every person to assess the effectiveness of obesity treatment.
No less important are nutrition, waist circumference, changes in body weight in dynamics, tolerability of therapy and physical activity.
Why is an individual approach more important than finding the strongest peptide?
One person responds well to a certain drug, another has severe nausea, a third faces a plateau, and a fourth, after significant weight loss, cannot maintain the result.
These are different situations that require different assessments.
It makes no sense to focus only on reviews, the popularity of the molecule or the maximum percentage of weight loss in the study.
It is important to understand what exactly prevents you from achieving the result: nutritional characteristics, concomitant diseases, side effects, incorrect expectations or the need to revise medical tactics.
At Nova Vroda, I pay attention not only to the number on the scale, but also to the reasons for weight gain, appetite, eating behavior, analyzes and maintaining the result.
My goal is to help you understand modern approaches to weight control, separate scientific data from marketing and understand which issues are worth discussing with your doctor.
After all, successful weight loss is not only about a lower number on the scale. It is also about preserving muscle, normal nutrition, well-being and long-term health.
About the author
Nova Vroda experts
nutritionist
Works with eating habits, daily routine and gradual lifestyle changes without extremes.
Sources
- 1.Amylin: A Multi-Functional Pancreatic Hormone — A Review (2026). Огляд фізіології аміліну, його впливу на насичення, спорожнення шлунка та харчову поведінку.
- 2.Garvey W. T. et al. Coadministered Cagrilintide and Semaglutide in Adults with Overweight or Obesity. NEJM, 2025. Дослідження REDEFINE 1: середнє зниження маси тіла на 20,4% за 68 тижнів у групі CagriSema.
- 3.Davies M. J. et al. Cagrilintide–Semaglutide in Adults with Overweight or Obesity and Type 2 Diabetes. NEJM, 2025. Дослідження REDEFINE 2 щодо зниження ваги та контролю глюкози при діабеті 2 типу.